In this post, we will cover everything you need to know about your menstrual cycle.
Key points covered:
The menstrual cycle starts with the first day of the period and ends the day before the next period begins
The brain, ovaries, and uterus work together and communicate through hormones (chemical signals sent through the blood from one part of the body to another) to keep the cycle going.
The first part of the cycle (follicular phase) prepares an egg to be released from the ovary and builds the lining of the uterus
The second part of the cycle (luteal phase) prepares the uterus and body to either accept a fertilized egg or to start the next cycle if pregnancy doesn’t occur
Important:
The menstrual cycle is more than just the period. In fact, periods are just the first part of your cycle.
Understanding the menstrual cycle is important because it can impact the body from head to toe. You can see changes in your hair skin, bowel movements, mental health, physical strength, libido, and so on.
Hormonal methods of birth control prevent some or all of the steps in the cycle from happening.
What is the menstrual cycle?
By definition, the menstrual cycle begins with the first day of your period, which is counted as ‘Day 1’ and ends just before the next period (bleeding).
It’s the female body’s way of preparing for a possible pregnancy every month.
Understanding your cycle is very important as it impacts every aspect of female well-being, including hunger and sleep.
As the hormones in your cycle change throughout the month, your body and mind also go through a number of changes.
How long is the menstrual cycle?
A menstrual cycle is often thought of as lasting 28 days, but regular cycles between 21 and 35 days can be normal, according to the NHS↗ (opens in a new tab). Cycle length varies from person to person, so get to know your own pattern rather than comparing it with someone else’s.
How many women have irregular cycles?
The NHS describes periods as irregular↗ (opens in a new tab) when the gap between their starts is less than 21 days or more than 35 days. Cycles are often more irregular in the years after periods begin and as menopause approaches.
A consistent 38-day cycle may be your usual pattern; the U.S. Office on Women’s Health↗ (opens in a new tab) uses a range of 24–38 days. Still, speak with a healthcare professional if your cycles regularly fall outside the NHS range, vary frequently, or your usual pattern changes.
What are the menstrual cycle phases?
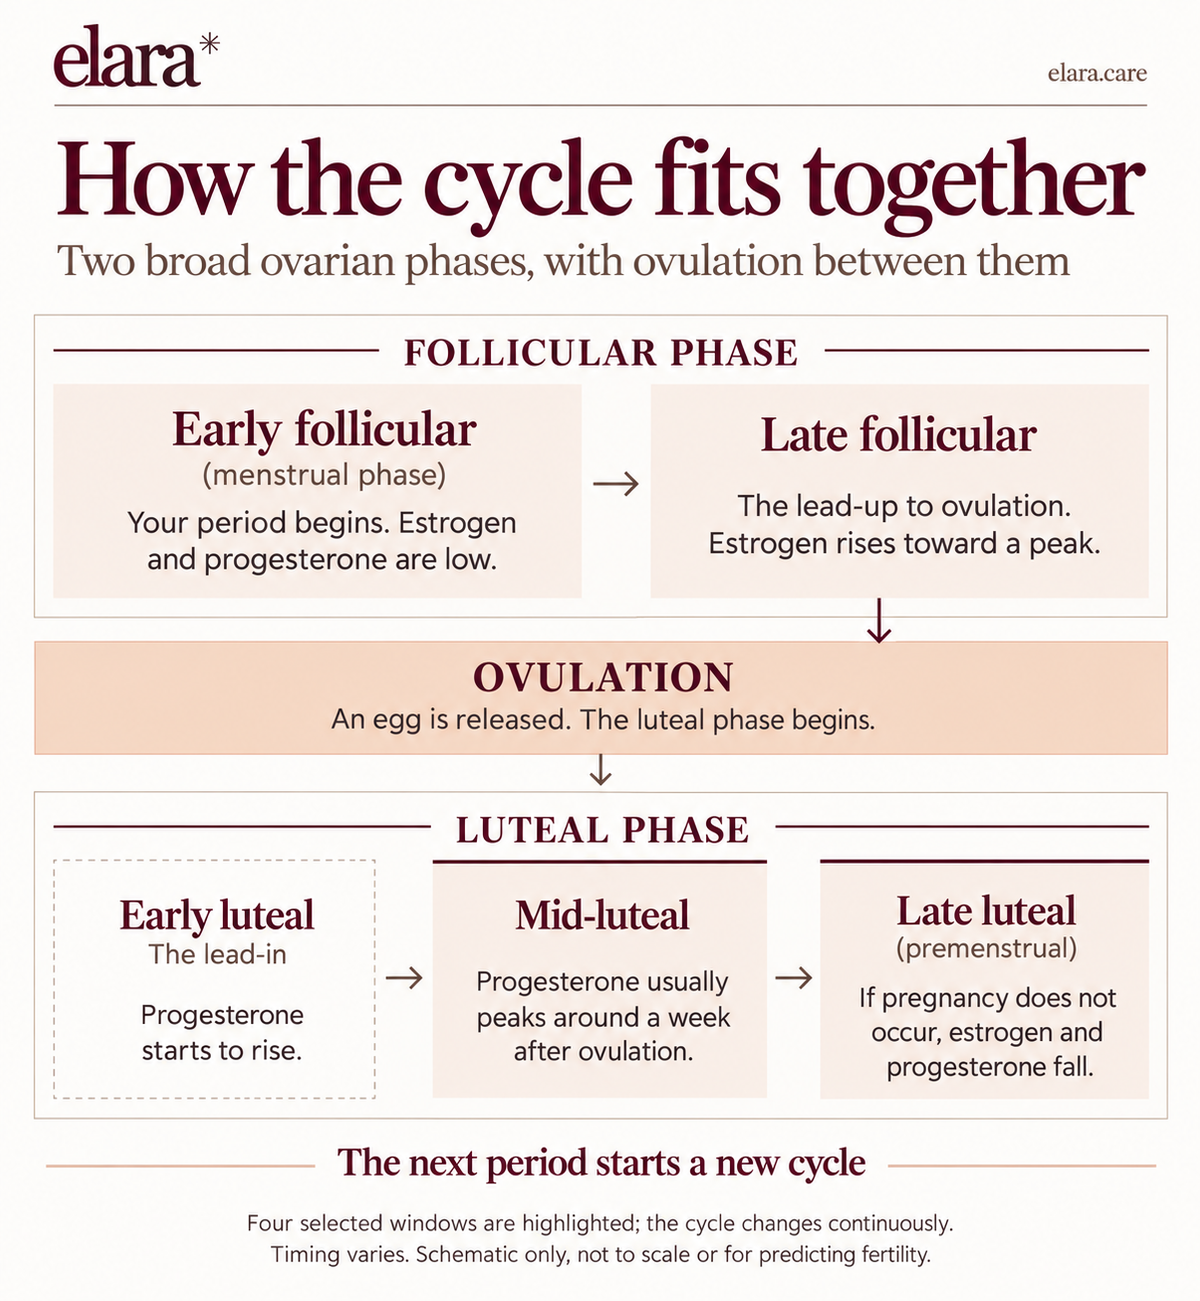
The ovarian cycle has two main phases: the follicular phase, from the first day of your period to ovulation, and the luteal phase, after ovulation until the next period. Ovulation marks the transition between them. For consistency with our cycle syncing guide, we explain four selected hormonal windows below: early follicular (menstrual), late follicular, mid-luteal and late luteal (premenstrual), with a separate explanation of ovulation. Researchers subdivide the cycle in different ways; this is not a universal four- or five-phase classification.
How the cycle fits together: four selected windows within two broad ovarian phases. Ovulation is the transition; early luteal is the lead-in to mid-luteal. Timing varies. · Elara Care · AI-assisted schematic illustration
When: The early follicular phase begins on the first day of your period. Bleeding usually lasts between 2 and 7 days. The whole follicular phase continues after your period finishes, right up to ovulation.
What happens: During the early follicular phase you shed your uterine lining (bleeding), and your estrogen and progesterone levels are low.
Possible symptoms: Abdominal cramps, fatigue, and brain fog. Experiences vary, and you may notice little change.
When: The final part of the follicular phase, in the lead-up to ovulation. Its timing varies between cycles.
What happens: During this phase, estrogen rises toward a peak before ovulation, while progesterone remains relatively low. Follicles develop in the ovaries during the follicular phase; each contains an immature egg, and usually one becomes the dominant follicle that releases its egg. Estrogen helps rebuild the uterine lining after menstruation. This rebuilding is called the proliferative phase of the uterine cycle; it overlaps the follicular phase of the ovarian cycle.
Possible symptoms: You may notice changes in energy or how you feel. Higher estrogen does not guarantee greater strength, mental focus or a better mood.
I feel like I have a lot more energy during this time. It's great for working out and sticking to my nutrition plan. However, the excess energy can sometimes make my mind feel like it's going at a million miles an hour, making it hard to concentrate on one thing. I've found that time blocking my work (scheduling it in my work calendar) helps me get things done.
Ovulation: the transition from follicular to luteal
When: Usually around 10–16 days before your next period. The date can change from cycle to cycle, and some cycles do not include ovulation.
What happens: Ovulation is the release of an egg from an ovary. It marks the end of the follicular phase and the start of the luteal phase. Estrogen peaks before ovulation and then falls. An increase in luteinizing hormone (LH), called an LH surge, helps trigger the egg’s release. Progesterone starts to rise afterward. Researchers may use “ovulatory” or “periovulatory” to describe a window around this event.
Possible symptoms: Some people notice changes in discharge or sex drive, or mild one-sided discomfort around ovulation; others notice little change. There is no universal peak in energy, confidence or sociability.
I take advantage of this time to meet up with friends. If possible I also try and schedule important meetings around this time as I feel much more positive. Like I can take over the world.
When: The middle part of the luteal phase, around a week after ovulation. The whole luteal phase starts after ovulation and ends the day before your next period; “mid-luteal” does not describe that entire span.
What happens: The body prepares for a possible pregnancy. Early in the luteal phase, the follicle that released the egg becomes the corpus luteum and produces progesterone and estrogen. Progesterone usually peaks about a week after ovulation, alongside a smaller second rise in estrogen. Progesterone helps prepare and maintain the uterine lining for a possible pregnancy.
Possible symptoms: Some women report PMS symptoms during the luteal phase, including fatigue or changes in mood. Progesterone can raise body temperature slightly, but the hormone pattern alone does not tell you how you will feel or how hard you can exercise.
I generally feel a lot warmer on the train, so wearing a few layers so that I can remove them, helps me stay comfortable. I also find that my brain slows down slightly, making it much easier to focus on tasks that require prolonged concentration.
When: The days before your next period. The timing varies; it is not a fixed day range for everyone.
What happens: If pregnancy does not occur, the corpus luteum breaks down and estrogen and progesterone fall. This hormone withdrawal leads to shedding of the uterine lining and the next period.
Possible symptoms:PMS can include mood swings, irritability, fatigue, bloating, breast tenderness, and sleep disturbances. Symptoms and their severity vary between people and cycles, and they can begin before the late luteal window.
Maintaining a routine really helps me stay consistent with my workouts. I'll do my best to get into the gym, even if I end up using the session to mobilize and stretch. However, on days when I'm feeling really tired, I prioritize sleep. I also make sure to eat protein with every meal and keep dark chocolate in my fridge for when I want a "dessert".
What hormones are involved in the menstrual cycle?
The menstrual cycle is regulated by several different hormones. But the main ones are:
Hormone
Main role in the cycle
Typical pattern
FSH (follicle-stimulating hormone)
Helps ovarian follicles grow; each contains an immature egg.
Rises as a new cycle approaches, then helps recruit follicles early in the follicular phase.
Estrogen (mainly estradiol)
Helps rebuild the uterine lining after menstruation.
Rises before ovulation, then has a smaller second rise during the luteal phase.
LH (luteinizing hormone)
An LH surge helps trigger egg release.
Surges before ovulation; afterward it supports the corpus luteum.
Progesterone
Helps prepare and maintain the uterine lining for a possible pregnancy.
Rises after ovulation, usually peaks mid-luteal, then falls if pregnancy does not occur.
This is a simplified pattern for a cycle with ovulation. Hormone levels and timing vary; the table cannot identify your phase or diagnose a hormone problem.
Breakdown of hormones and their functions in the menstrual cycle
Follicle stimulating hormone
Follicle-stimulating hormone is produced by the pituitary gland. It regulates the functions of both the ovaries and the testes. Lack or insufficiency of it can cause infertility in both men and women.
What is a follicle-stimulating hormone?
Follicle-stimulating hormone is one of the gonadotropic hormones, the other being the luteinizing hormone, and both are released by the pituitary gland into the bloodstream.
Follicle-stimulating hormone is essential to pubertal development. In women, this hormone stimulates the growth of ovarian follicles in the ovary before the release of an egg and it also increases a type of estrogen.
Estrogen
What is estrogen?
Estrogen is one of the main female sex hormones. While both women and men produce estrogen, it plays a bigger role in women’s bodies.
There are three estrogens – estrone, estradiol, and estriol – the most potent of which is estradiol.
Estradiol is produced in women of childbearing age, mostly by the ovaries.
Estriol is the main estrogen produced during pregnancy, mostly in the placenta.
Estrone, produced by the adrenal glands and fatty tissue, is the only type of estrogen produced after menopause.
Estradiol
What is estradiol?
Estradiol is a steroid hormone made from cholesterol and is the strongest of the three naturally produced estrogens. It is the main estrogen found in women and has many functions, although it mainly acts to mature and maintain the female reproductive system. A natural increase in blood estradiol concentrations during the menstrual cycle causes an egg to mature and be released.
Another important role of estradiol is to thicken the lining of the uterus so that the egg can implant if it becomes fertilized. Estradiol also promotes the development of breast tissue and increases both bone and cartilage density.
In premenopausal women, estradiol is mostly made by the ovaries. Estradiol levels vary throughout the menstrual cycle, rising to a peak before ovulation and showing a smaller second rise in the luteal phase. Levels are relatively low during menstruation. Estradiol levels change during the transition to menopause and are generally lower afterward. In pregnant women, the placenta also produces estradiol, especially toward the end of pregnancy.
Men also produce estradiol; however, the amounts produced are much lower than in women. Within the testes, some testosterone is changed into estradiol and this estradiol is essential for the production of sperm. In both sexes, estradiol is also made in much smaller amounts by fat tissue, the brain, and the walls of blood vessels.
Luteinizing hormone
What is the luteinizing hormone?
Luteinizing hormone, like a follicle-stimulating hormone, is a gonadotrophic hormone produced and released by cells in the anterior pituitary gland.
It is crucial in regulating the function of the testes in men and ovaries in women.
In women, luteinizing hormone carries out different roles during the follicularandluteal phases. During the follicularphase,it helps the ovarian follicles produce hormones involved in the cycle, including estradiol.
An LH surge helps trigger the release of a mature egg from the ovary, a process called ovulation. This marks the transition from the follicular to the luteal phase; it does not always happen on day 14.
After ovulation, the remnants of the ovarian follicle form a corpus luteum.
The luteinizing hormone stimulates the corpus luteum to produce progesterone, which is required to support the early stages of pregnancy if fertilization occurs.
Progesterone
What is progesterone?
Progesterone belongs to a group of steroid hormones called progestogens. It is mainly secreted by the corpus luteum in the ovary during the luteal phase of the menstrual cycle.
It plays an important role in the menstrual cycle and in maintaining the early stages of pregnancy.
During the menstrual cycle, when an egg is released from the ovary at ovulation, the remnants of the ovarian follicle that enclosed the developing egg form a structure called the corpus luteum. This releases progesterone and estrogen. Progesterone usually peaks around a week after ovulation, in the mid-luteal phase.
Progesterone prepares the body for pregnancy in the event that the released egg is fertilized.
If pregnancydoes not occur, the corpus luteum breaks down during the late luteal phase, progesterone and estrogen fall, and the next period begins.
If the egg is fertilized, progesterone stimulates the growth of blood vessels that supply the lining of the womb (endometrium) and stimulates glands in the endometrium to secrete nutrients that nourish the early embryo.
Progesterone then prepares the tissue lining of the uterus to allow the fertilized egg to implant and helps to maintain the endometrium throughout pregnancy.
During the early stages of pregnancy, progesterone is still produced by the corpus luteum and is essential for supporting the pregnancy and establishing the placenta. Once the placenta is established, it then takes over progesterone production at around weeks 8-12 of pregnancy.
During pregnancy, progesterone plays an important role in the development of the fetus; it stimulates the growth of maternal breast tissue; prevents lactation; and strengthens the pelvic wall muscles in preparation for labor.
The level of progesterone in the body steadily rises throughout pregnancy until labor occurs and the baby is born.
Although the corpus luteum in the ovaries is the major site of progesterone production in humans, progesterone is also produced in smaller quantities by the ovaries themselves, the adrenal glands, and, during pregnancy, the placenta.
Conclusion
Your menstrual cycle is your personal algorithm of life. Take time to learn about how changing hormones impact you throughout the cycle (we call this menstrual cycle literacy) to understand how you can take advantage of your hormones instead of suffering through them.
You might also be interested in the following article:
Fraser IS, Critchley HO, Broder M, Munro MG. The FIGO recommendations on terminologies and definitions for normal and abnormal uterine bleeding. Semin Reprod Med. 2011;29(5):383-90.
Munster K, Schmidt L, Helm P. Length and variation in the menstrual cycle-a cross-sectional study from a Danish county. BJOG. 1992;99(5): 422–9.
Treloar AE, Boynton RE, Behn BG, Brown BW. Variation of the human menstrual cycle through reproductive life. Int J Fertil. 1967;12(1 Pt 2):77-126.
Fehring RJ, Schneider M, Raviele K. Variability in the phases of the menstrual cycle. JOGNN. 2006;35: 376-384.
Explore the findings and sources for each recommendation.
Elara EvidenceIndependent review pending
7 claims assessed
These notes explain the research and guidance behind the article, what they support and where uncertainty remains.
Which claims were assessed
Seven assessments cover the phase terminology, physiological timing and hormone summary, including a separate explanation for each of the five windows described here. They do not establish phase-specific diet, workout or productivity schedules, or turn personal experiences into research evidence.
How Elara assesses evidence
Confidence describes how certain we are about a research finding. It does not measure how healthy a food is, or promise that it will work for you.
Understanding the physiological sequence without fixed day ranges or individual symptom predictionsEvidence is indirectEvidence is indirect
Question. Cycle phases, timing and terminology and Understanding the physiological sequence without fixed day ranges or individual symptom predictions in Readers learning about natural ovulatory cycles.
Finding. This update uses the same phase definitions as the Cycle Syncing article. The broad ovarian phases are follicular and luteal; menstruation overlaps early follicular, and ovulation marks the transition. Early follicular, late follicular, mid-luteal and late luteal are selected windows, with early luteal explained as the lead-in to mid-luteal. Researchers use different subdivisions, so the five explanation sections are not a universal scientific classification.
The 2021 working guide describes several classification schemes and proposes four research hormone profiles; McNulty’s 2020 review uses six categories. The 2026 follow-up retains numbered profiles and distinguishes hormonal sampling from symptom-based windows. These methodological sources explain terminology; they do not establish a fixed food, workout or work-performance schedule.
Timing and symptoms: NHS guidance describes regular cycles of 21–35 days, bleeding usually lasting 2–7 days, and ovulation often 10–16 days before the next period. These ranges do not confirm an individual’s ovulation day. Symptoms vary, and PMS can start before the late luteal window. Practical exercise and food examples are flexible choices; the team’s personal experiences are not predictions for every reader.
Evidence label. Evidence is indirect
Applicability. Evidence is indirect — These sources explain typical physiology and research terminology. They do not identify an individual’s hormonal phase or predict their symptoms, fertility or response to exercise.
Why no grade. This is a physiological explanation supported by endocrinology guidance and research-method papers, not a graded treatment-effect claim.
Rationale. The explanation uses the same broad follicular/luteal division and selected hormonal windows as the Cycle Syncing article. Ovulation marks the transition; early luteal leads into mid-luteal.
Limitations. Cycle timing and symptoms vary. These sources do not validate a fixed calendar or phase-specific food, workout or work-performance schedule. The update was a targeted terminology and physiology check, not a new comprehensive appraisal of every hormone claim in the article.
Safety context. The table and graphic cannot identify an individual’s phase, diagnose a hormone problem or predict fertility. Symptoms that affect daily life, irregular bleeding or a changed pattern warrant clinical advice.
Search. Targeted editorial checks of the supplied citations on October 29 and November 1, 2026, followed by reconciliation with the accepted article. This was not a systematic review or a formal GRADE assessment. Access limitations from that review are retained. Searched through .
Understanding the physiological sequence without fixed day ranges or individual symptom predictionsEvidence is indirectEvidence is indirect
Question. Hormone roles in an ovulatory cycle and Understanding the physiological sequence without fixed day ranges or individual symptom predictions in Readers learning about natural ovulatory cycles.
Finding. Hormone summary and shared schematic: Society for Endocrinology guidance explains follicle growth, the LH surge, the corpus luteum and the uterine lining. These sources support the physiological sequence, not a fixed calendar or predictions about symptoms, performance or fertility. The table condenses the hormone roles explained above; it is not a diagnostic guide.
Evidence label. Evidence is indirect
Applicability. Evidence is indirect — These sources explain typical physiology and research terminology. They do not identify an individual’s hormonal phase or predict their symptoms, fertility or response to exercise.
Why no grade. This is a physiological explanation supported by endocrinology guidance and research-method papers, not a graded treatment-effect claim.
Rationale. The explanation uses the same broad follicular/luteal division and selected hormonal windows as the Cycle Syncing article. Ovulation marks the transition; early luteal leads into mid-luteal.
Limitations. Cycle timing and symptoms vary. These sources do not validate a fixed calendar or phase-specific food, workout or work-performance schedule. The update was a targeted terminology and physiology check, not a new comprehensive appraisal of every hormone claim in the article.
Safety context. The table and graphic cannot identify an individual’s phase, diagnose a hormone problem or predict fertility. Symptoms that affect daily life, irregular bleeding or a changed pattern warrant clinical advice.
Search. Targeted editorial checks of the supplied citations on October 29 and November 1, 2026, followed by reconciliation with the accepted article. This was not a systematic review or a formal GRADE assessment. Access limitations from that review are retained. Searched through .
Participants were followed for up to two cycles; this does not establish everyone’s longer-term pattern.[14]Section cited: Methods: Study design↗
Question. Early follicular phase (menstrual phase) and Does menstruation occur in the early follicular phase, and what happens to reproductive hormones? in Readers learning about naturally occurring ovulatory menstrual cycles over The relevant window within a menstrual cycle.
Finding. Menstruation begins the follicular phase. Estrogen and progesterone are low around this window, and the uterine lining sheds. The follicular phase continues after bleeding ends.
Evidence label. Moderate confidence
Applicability. Directly applicable
Rationale. The onset of menstruation and the low-steroid early follicular pattern are supported by the Endotext physiology chapter. The prospective US BioCycle bleeding report adds directly observed menstrual patterns, but only in selected healthy adults followed for up to two cycles. The exact 2–7-day range is guidance from NHS, not an estimate established by that cohort. Moderate confidence is proposed for the combined physiology-and-timing explanation: support is coherent, while population coverage and the limits of a typical bleeding range leave uncertainty. This is an editorial judgment under Elara Evidence 0.1, not a formal GRADE rating or a prediction of symptoms.
Limitations. Bleeding duration and hormone-based research windows are different measures. The US BioCycle study found a median bleeding duration of five days in selected healthy adults; it does not establish the exact 2–7-day range cited from NHS guidance. Its observations cover up to two cycles. These sources do not predict fatigue, brain fog or exercise tolerance for an individual.
Safety context. These explanations cannot identify an individual’s phase or diagnose a hormone problem. Seek professional advice for symptoms that disrupt daily life or a changed bleeding pattern.
Search. Targeted editorial source check on November 2, 2026, prioritising US specialist guidance and peer-reviewed primary research. Relevant Endotext, ASRM, BioCycle and Office on Women’s Health sections were inspected. Existing numerical ranges retain their matched NHS source. This was not a systematic review or formal GRADE assessment. Searched through .
What happens to estrogen, follicles and the uterine lining before ovulation?Confidence: Moderate
What these icons tell you
Hormones measured
The BioCycle study measured reproductive hormones across the cycle. It did not test phase-based productivity, meal or workout schedules.[15]Section cited: Hormone profiles Figure 1↗
Selected participants
The BioCycle participants were selected healthy, regularly menstruating adults aged 18–44. The findings should not be assumed to describe irregular cycles, anovulation or hormonal contraception.[15]Section cited: Methods: Study population↗
Question. Late follicular phase and What happens to estrogen, follicles and the uterine lining before ovulation? in Readers learning about naturally occurring ovulatory menstrual cycles over The relevant window within a menstrual cycle.
Finding. Before ovulation, a dominant follicle develops and estrogen rises while progesterone remains relatively low. Estrogen supports rebuilding of the uterine lining.
Evidence label. Moderate confidence
Applicability. Directly applicable
Rationale. Endotext explains dominant-follicle development, rising estradiol and estrogen-driven rebuilding of the uterine lining. The BioCycle study supplies serial hormone measurements consistent with the rising estrogen pattern, but does not directly measure endometrial rebuilding. Moderate confidence is proposed for this combined explanation: the physiology is supported, while the observational evidence comes from selected healthy, regularly menstruating adults and late-follicular boundaries vary. This is an editorial judgment under Elara Evidence 0.1, not a formal GRADE rating. It does not grade claims about mood, concentration or exercise.
Limitations. Research definitions of the late follicular window vary. The BioCycle study followed selected healthy, regularly menstruating adults for up to two cycles. Hormone patterns do not predict a person’s mood, concentration or exercise performance.
Safety context. These explanations cannot identify an individual’s phase or diagnose a hormone problem. Seek professional advice for symptoms that disrupt daily life or a changed bleeding pattern.
Search. Targeted editorial source check on November 2, 2026, prioritising US specialist guidance and peer-reviewed primary research. Relevant Endotext, ASRM, BioCycle and Office on Women’s Health sections were inspected. Existing numerical ranges retain their matched NHS source. This was not a systematic review or formal GRADE assessment. Searched through .
Ovulation: the transition from follicular to luteal
What is ovulation, and how does it connect the follicular and luteal phases?Confidence: Moderate
What these icons tell you
Hormones measured
The BioCycle study measured reproductive hormones across the cycle. It did not test phase-based productivity, meal or workout schedules.[15]Section cited: Hormone profiles Figure 1↗
Selected participants
The BioCycle participants were selected healthy, regularly menstruating adults aged 18–44. The findings should not be assumed to describe irregular cycles, anovulation or hormonal contraception.[15]Section cited: Methods: Study population↗
Question. Ovulation: the transition from follicular to luteal and What is ovulation, and how does it connect the follicular and luteal phases? in Readers learning about naturally occurring ovulatory menstrual cycles over The relevant window within a menstrual cycle.
Finding. Ovulation releases an egg between the follicular and luteal phases. Estrogen rises before it, an LH surge precedes the release, and progesterone becomes higher in the luteal phase.
Evidence label. Moderate confidence
Applicability. Directly applicable
Rationale. Endotext describes the LH surge, egg release and transition to corpus-luteum activity; BioCycle supplies serial hormone measurements and an estimate of ovulation timing. NHS guidance supports the retained 10–16-day interval before the next period. That interval is a typical range, not a way to establish an individual's ovulation date. Moderate confidence is proposed for the combined sequence-and-timing explanation because the physiology is coherent but timing and ovulation ascertainment are variable. This is an editorial judgment under Elara Evidence 0.1, not a formal GRADE rating or a fertility prediction.
Limitations. Cycle timing varies. The existing 10–16-day interval before the next period comes from NHS guidance; the US sources support the physiological sequence without establishing those exact limits. Hormone patterns do not demonstrate a universal peak in energy or sociability.
Safety context. These explanations cannot identify an individual’s phase or diagnose a hormone problem. Seek professional advice for symptoms that disrupt daily life or a changed bleeding pattern.
Search. Targeted editorial source check on November 2, 2026, prioritising US specialist guidance and peer-reviewed primary research. Relevant Endotext, ASRM, BioCycle and Office on Women’s Health sections were inspected. Existing numerical ranges retain their matched NHS source. This was not a systematic review or formal GRADE assessment. Searched through .
What is mid-luteal timing, and how do corpus-luteum hormones affect the uterine lining?Confidence: Moderate
What these icons tell you
Hormones measured
The BioCycle study measured reproductive hormones across the cycle. It did not test phase-based productivity, meal or workout schedules.[15]Section cited: Hormone profiles Figure 1↗
Selected participants
The BioCycle participants were selected healthy, regularly menstruating adults aged 18–44. The findings should not be assumed to describe irregular cycles, anovulation or hormonal contraception.[15]Section cited: Methods: Study population↗
Question. Mid-luteal phase and What is mid-luteal timing, and how do corpus-luteum hormones affect the uterine lining? in Readers learning about naturally occurring ovulatory menstrual cycles over The relevant window within a menstrual cycle.
Finding. The corpus luteum produces progesterone after ovulation. ASRM describes a usual peak 6–8 days afterward; this supports the article’s “around a week.” Estrogen also has a second rise, and progesterone supports the uterine lining.
Evidence label. Moderate confidence
Applicability. Directly applicable
Rationale. The 2026 ASRM committee opinion explicitly describes progesterone peaking 6–8 days after ovulation and the variability caused by pulsatile secretion. Endotext supports corpus-luteum hormone production and the smaller luteal estrogen rise; BioCycle provides serial hormone observations. Moderate confidence is proposed for the combined explanation: these sources support 'around a week' and the broad physiological pattern, but cannot determine a person's peak or hormone level from a calendar. This is an editorial judgment under Elara Evidence 0.1, not a formal GRADE rating or validation of luteal-phase testing.
Limitations. Mid-luteal is a window within the whole luteal phase. ASRM’s clinical guidance describes typical physiology; calendar dates cannot establish an individual’s progesterone level or exercise capacity. The BioCycle observations came from selected healthy, regularly menstruating adults.
Safety context. These explanations cannot identify an individual’s phase or diagnose a hormone problem. Seek professional advice for symptoms that disrupt daily life or a changed bleeding pattern.
Search. Targeted editorial source check on November 2, 2026, prioritising US specialist guidance and peer-reviewed primary research. Relevant Endotext, ASRM, BioCycle and Office on Women’s Health sections were inspected. Existing numerical ranges retain their matched NHS source. This was not a systematic review or formal GRADE assessment. Searched through .
What happens to reproductive hormones before the next period, and how do premenstrual symptoms vary?Confidence: Moderate
What these icons tell you
Hormones measured
The BioCycle study measured reproductive hormones across the cycle. It did not test phase-based productivity, meal or workout schedules.[15]Section cited: Hormone profiles Figure 1↗
Selected participants
The BioCycle participants were selected healthy, regularly menstruating adults aged 18–44. The findings should not be assumed to describe irregular cycles, anovulation or hormonal contraception.[15]Section cited: Methods: Study population↗
Question. Late luteal phase (premenstrual phase) and What happens to reproductive hormones before the next period, and how do premenstrual symptoms vary? in Readers learning about naturally occurring ovulatory menstrual cycles over The relevant window within a menstrual cycle.
Finding. Without pregnancy, corpus-luteum function declines, estrogen and progesterone fall, and the next period follows. Premenstrual symptoms vary; some people have little change and others need help when symptoms affect daily life.
Evidence label. Moderate confidence
Applicability. Directly applicable
Rationale. Endotext supports corpus-luteum regression, falling ovarian steroids and the onset of menstruation when pregnancy does not occur. BioCycle adds observed cycle-level hormone patterns. Office on Women's Health guidance supports variation in premenstrual symptoms, while acknowledging uncertainty about why PMS occurs. Moderate confidence is proposed for this combined physiology-and-symptom explanation: the broad pattern is supported, but the timing and experience of symptoms differ and are not predicted by these studies. This is an editorial judgment under Elara Evidence 0.1, not a formal GRADE rating or a causal claim about an individual's symptoms.
Limitations. The exact late-luteal boundary is not fixed, and premenstrual symptoms can start earlier in the luteal phase. These sources explain physiology and symptom variability; they do not establish a phase-specific workout, meal or work schedule.
Safety context. These explanations cannot identify an individual’s phase or diagnose a hormone problem. Seek professional advice for symptoms that disrupt daily life or a changed bleeding pattern.
Search. Targeted editorial source check on November 2, 2026, prioritising US specialist guidance and peer-reviewed primary research. Relevant Endotext, ASRM, BioCycle and Office on Women’s Health sections were inspected. Existing numerical ranges retain their matched NHS source. This was not a systematic review or formal GRADE assessment. Searched through .
Founder of Elara Care and O.A. Dip. Certified Women's Health Practitioner, Jas is working to create better solutions for women since 2018, sharing her struggles and experiences with female health