
ABOUT THE AUTHOR
Stacie Brett
Stacie Brett writes and edits content for women’s health brands. She helps make articles and web pages easier to find and understand, focusing on the questions women want answered.
Full profile and articles ↗The luteal phase is the part of your cycle after ovulation (the release of an egg) and before your next period.
Expert reviewed by Jasveer Matharu · 27 October 2026
Added evidence summaries for 6 recommendations.
Updated the luteal-phase explainer, cycle diagram, clinical guidance and sources; credited Stacie Brett as writer and editor.
First published

The luteal phase is the second half of your menstrual cycle. It starts after you ovulate and ends when your next period begins, and it usually lasts around two weeks. During this time, levels of a hormone called progesterone rise to prepare your womb for a possible pregnancy. If pregnancy doesn’t happen, those levels fall again, triggering your period.
Key points:
You may have come across a few different names for the stages of your cycle. When describing what happens in the ovaries, we use two main phases: follicular and luteal. You may also see it described in four stages, with your period and ovulation named separately.
The first half, the follicular phase, runs from the first day of your period until ovulation. The luteal phase is everything after that: it begins once an egg has been released and ends when your next period starts.
Before ovulation, an egg develops inside a small sac called a follicle. After releasing the egg, that sac becomes a temporary gland that makes progesterone (opens in a new tab). This gland is the corpus luteum (Latin for “yellow body”), and it’s where the luteal phase gets its name.
You might also see this part of the cycle broken down a little further:
You can find out more about all the phases in our article The Menstrual Cycle - Phases, Hormones, and Their Functions.
Think of it as the two weeks or so leading up to your period. In an example 28 day cycle, with ovulation around day 14, that puts the luteal phase at roughly days 15 to 28.
Keep in mind that real cycles vary more than that example suggests. The NHS describes regular cycles of 21 to 35 days as normal (opens in a new tab), and ovulation doesn’t always land on day 14. The gap between ovulation and your period is generally more consistent (opens in a new tab) than the first half of the cycle, but it can vary too.
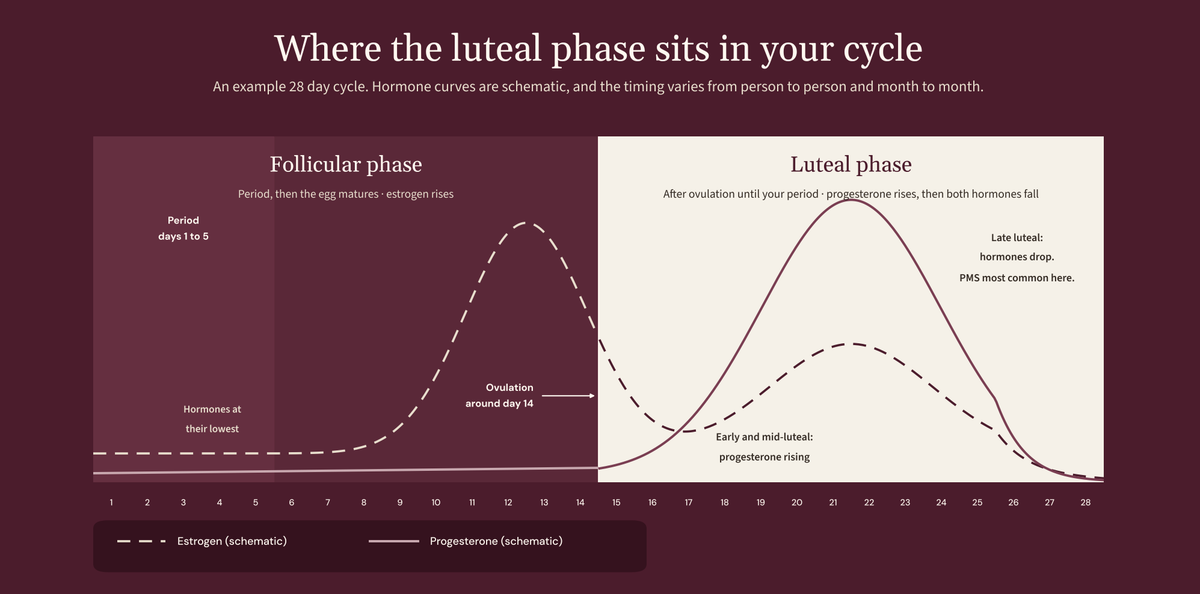
View full-size diagram (opens in a new tab)
If you use hormonal contraception that stops ovulation, such as the combined pill (opens in a new tab), you won’t have a luteal phase in the usual sense, because there’s no ovulation for it to follow. The bleed you get on a pill break isn’t the same as a natural period.
After ovulation, the empty follicle in your ovary turns into the corpus luteum and starts producing progesterone, along with a smaller amount of estrogen. This is the big hormonal shift of the luteal phase: the first half of your cycle is led by estrogen, the second half by progesterone.
Estrogen has already helped your womb lining grow during the first half of the cycle. Progesterone then helps prepare and maintain that lining (opens in a new tab) so a fertilised egg can attach. This attachment is called implantation. It also raises your body temperature slightly and changes your cervical mucus (opens in a new tab), the fluid made by your cervix, which becomes thicker and less stretchy after ovulation.
If no fertilized egg implants, the corpus luteum breaks down after around two weeks (opens in a new tab). Progesterone and estrogen both fall, the womb lining can no longer be maintained, and it’s shed as your period.
If a fertilized egg does implant, the corpus luteum keeps going and progesterone stays high, which is why a missed period is often the first sign of pregnancy.
For most people the luteal phase lasts somewhere between 10 and 16 days, with 12 to 14 days being typical (opens in a new tab).
If you notice a similar gap between ovulation and your period across several cycles, that can help you estimate when your next period might arrive. Give that estimate a little flexibility, though. Your period may not arrive on exactly the day you expect.
A luteal phase of fewer than 10 days is generally considered short (opens in a new tab), although clinical definitions vary. A short phase can also occur in people without fertility problems (opens in a new tab). Seeing a shorter gap in your notes doesn’t automatically mean you have low progesterone or will struggle to get pregnant.
Some conditions that affect ovulation or progesterone have been associated with luteal-phase problems (opens in a new tab), including thyroid conditions, eating disorders and PMOS (polyendocrine metabolic ovarian syndrome) also known as PCOS. If you repeatedly notice a short gap between ovulation and your period, especially while trying to conceive, talk it through with your GP.
If your period hasn’t arrived when you expected, think back to how you worked out your ovulation date. It may have happened later than you thought. Pregnancy is another possibility: if your period is late and pregnancy is possible, you can test from the first day of a missed period (opens in a new tab). If you don’t know when your period is due, test at least 21 days after the last time you had unprotected sex.
If pregnancy tests are negative and your cycles keep getting longer or more irregular, your GP can help you work out what’s going on. Irregular cycles have many causes, including PMOS, thyroid problems, stress and perimenopause (opens in a new tab).
You’re in your luteal phase after ovulation. One way to get a sense of whether you’ve reached this stage is to track your temperature each morning.
This means using a thermometer to take your temperature as soon as you wake up, before you get out of bed, and recording it each day. This waking, resting temperature is called your basal body temperature. It usually rises slightly after ovulation (opens in a new tab).
You’re looking for a small rise that stays up over several days, rather than a single higher reading. That pattern can suggest that ovulation has already happened and you’re now in your luteal phase. It’s a clue rather than an exact test, and it won’t tell you in advance when you’re going to ovulate.
Some people also feel a mild, one-sided ache around ovulation, sometimes called ovulation pain (opens in a new tab) or mittelschmerz. Not everyone gets it, and pain alone can’t confirm when you’ve ovulated. Other conditions can cause similar pain, so get medical advice if it’s severe, keeps coming back or you think you might be pregnant.
If you’d like to keep track, there are a few ways to get a clearer picture. Each gives you a different clue: some suggest ovulation is approaching, while others point to it having already happened.
If you’re using fertility awareness to avoid pregnancy, an app prediction or one symptom isn’t enough (opens in a new tab) to tell you that sex without contraception is safe.
You might notice changes in how you feel before your period, or you might notice very little. PMS symptoms can occur in the weeks beforehand, and the mix can change from one month to the next.
The symptoms the NHS lists as common in PMS include (opens in a new tab):
There’s no particular mood or energy level you’re supposed to have at this point in your cycle. If you want to understand your own pattern, jot down what you notice. If a symptom is new, keeps coming back or makes your day harder, talk it through with your GP.
If tiredness is the symptom that bothers you most, we’ve written about it in detail, including what may be behind it and what you can try:
If you feel very low, anxious or irritable in the week or two before your period, then begin to feel better a few days after it starts, that pattern can be premenstrual dysphoric disorder (PMDD) (opens in a new tab). Your GP can help you understand what’s happening and talk through the support available.
The luteal phase helps prepare your womb for a possible pregnancy. If pregnancy doesn’t happen, falling hormone levels allow the lining to shed as your period. Knowing about this part of your cycle may help you make sense of changes you notice. You don’t need to treat its length as a score for your health or fertility.
Progesterone helps the womb lining support implantation and early pregnancy. But a calendar estimate or one progesterone result can’t tell you the whole story about fertility (opens in a new tab). If you’re concerned, your GP can look at your cycle and medical history and discuss whether tests would be useful.
You don’t have to be trying for a baby to find cycle tracking useful. A few notes about your period, sleep and symptoms may help you spot patterns and leave a little breathing room on days that tend to feel harder. The NHS recommends a symptom diary for at least two cycles (opens in a new tab) when looking into PMS. You can bring those notes to an appointment, so you don’t have to remember everything on the spot.
Here’s how the two halves of your cycle compare. The hormone changes follow a general pattern, but how you feel may be different from someone else.
| Follicular phase | Luteal phase | |
|---|---|---|
| When | First day of your period until ovulation | Ovulation until the first day of your next period |
| Typical length | Varies a lot; this is where cycle length differences usually come from | Around two weeks; the NHS gives about 10 to 16 days, with some variation |
| Main hormone | Estrogen, rising to a peak just before ovulation | Progesterone, rising to a peak then falling before your period |
| What’s happening | The womb lining rebuilds and an egg matures | Progesterone helps prepare and maintain the womb lining; falling hormones trigger a period if there’s no pregnancy |
| How it can feel | You may notice changes in energy or mood, or little difference | PMS symptoms can occur before your period; timing and severity vary |
Based on an example 28 day cycle. Experiences differ between people and between cycles.
If the days before your period feel harder, a few small adjustments may help. Start with what feels manageable:
For more on using food to support yourself in this phase, see What to Eat During the Luteal Phase.
You don’t have to dismiss symptoms just because they happen around your period. Speak to your GP if:
Yes, around the start: an egg can survive for about 24 hours after ovulation (opens in a new tab), and sperm from sex in the preceding days may still be present. But it’s easy to misjudge when ovulation happened.
No. Fourteen days is a guide, not a rule. The NHS describes a gap of about 10 to 16 days between ovulation and your period. If yours repeatedly seems unusually short, or your cycle changes, discuss it with your GP.
Not reliably. Tiredness and tender breasts can happen before a period and in early pregnancy (opens in a new tab), so symptoms alone can’t give you an answer. If your period is late and pregnancy is possible, take a test.
You may hear this called luteal phase deficiency. The idea is that, after ovulation, progesterone may not support the womb lining well enough or for long enough. Specialists still debate how to diagnose it (opens in a new tab), and it hasn’t been shown to cause infertility on its own. A short cycle or one hormone test isn’t enough to tell you that you have it.
If your contraception stops ovulation, such as the combined pill (opens in a new tab), you don’t have a luteal phase in the usual sense. Other methods work differently: most people using a hormonal coil continue to ovulate (opens in a new tab), so they may still have a luteal phase. Ask your doctor, nurse or pharmacist if you’re unsure how your method affects your cycle.
Not necessarily. A 2023 review brought together earlier reviews of the research and found mixed results and limitations in the studies (opens in a new tab). The authors concluded it was too early to say that hormone changes during the cycle make a meaningful difference to strength or muscle growth. If you feel you have less in the tank, adjust your workout; if you feel good, there’s no need to assume you’ll be weaker. Read more: Does the menstrual cycle impact women’s muscle strength performance in resistance training?
When your next period begins. Falling progesterone levels trigger the womb lining to shed, and the first day of bleeding marks day one of your new cycle.
If you’d like to, share what you notice in the comments below.
Explore the findings and sources for each recommendation.
We checked selected research claims about cycle tracking, luteal-phase deficiency, temperature, PMS exercise and strength.
Each explanation separates the finding from what it cannot tell us.
This draft contains 5 research assessments. Clinical self-care and safety advice is linked to guidance and checked separately in the review notes. It is not a systematic review or medical approval of the article.
Confidence describes how certain we are about a research finding. It does not measure how healthy a food is, or promise that it will work for you.
Search check: Targeted verification of the supplied article citations and relevant clinical guidance on October 27, 2026. This was not a systematic literature search or a formal GRADE review. Access limits and correction notices are recorded for each source; absence of a notice is not a guarantee. Searched through .
What the confidence labels meanMost trials had high risk of bias, results varied substantially, and programs lasted 8–12 weeks. None restricted exercise to the luteal phase. These results do not establish a best workout or a need to push through exhaustion. [20] Section cited: Primary outcome; Strengths and limitations; Intervention characteristics
Question. Regular exercise compared with non-exercise control and Overall premenstrual symptoms in Women with PMS in the included trials.
Finding. Regular exercise may reduce PMS symptoms. It is not established as an immediate treatment for luteal-phase exhaustion.
Evidence label. Limited confidence
Applicability. Directly applicable
Rationale. The review included 15 trials with 717 participants. Seven trials, with 265 participants, contributed to the pooled overall symptom result.
Limitations. Most trials had high risk of bias, results varied substantially, and programs lasted 8–12 weeks. None restricted exercise to the luteal phase. These results do not establish a best workout or a need to push through exhaustion.
Safety context. Discuss persistent or disabling symptoms with a qualified clinician. These findings do not replace assessment or establish a personal diagnosis.
Method. Elara Evidence method, version 0.1.
Independent review pending
Search. Targeted verification of the supplied article citations and relevant clinical guidance on October 27, 2026. This was not a systematic literature search or a formal GRADE review. Access limits and correction notices are recorded for each source; absence of a notice is not a guarantee. Searched through .
Measurement site, illness, sleep and environment affect readings. Wrist skin temperature is not core temperature. This does not predict an exact ovulation date, establish safe contraceptive days or prove a cause of fatigue. [19] Section cited: Effect of the menstrual cycle on core body temperature; Determining menstrual cycle phase
Question. Hormone changes in ovulatory cycles and Core temperature after ovulation and retrospective cycle clues in Naturally menstruating women in physiology studies.
Finding. Core temperature is commonly higher after ovulation. A sustained rise can provide a retrospective clue that ovulation occurred.
Evidence label. Moderate confidence
Applicability. Directly applicable
Rationale. The review describes an increase of about 0.3–0.7°C compared with the follicular phase, particularly evident during sleep or on waking.
Limitations. Measurement site, illness, sleep and environment affect readings. Wrist skin temperature is not core temperature. This does not predict an exact ovulation date, establish safe contraceptive days or prove a cause of fatigue.
Safety context. Discuss persistent or disabling symptoms with a qualified clinician. These findings do not replace assessment or establish a personal diagnosis.
Method. Elara Evidence method, version 0.1.
Independent review pending
Search. Targeted verification of the supplied article citations and relevant clinical guidance on October 27, 2026. This was not a systematic literature search or a formal GRADE review. Access limits and correction notices are recorded for each source; absence of a notice is not a guarantee. Searched through .
This assessment uses the committee’s synthesis; its underlying studies were not individually reappraised here. It does not dismiss symptoms or known endocrine conditions and cannot diagnose an individual. [5] Section cited: PROPOSED DIAGNOSTIC TESTS FOR LPD; POTENTIAL CLINICAL IMPLICATIONS OF LPD
Question. A short luteal phase or one progesterone result and Diagnosis of isolated luteal phase deficiency and prediction of infertility in People assessing their own cycle or fertility.
Finding. A short luteal phase or one progesterone result cannot establish a fertility diagnosis on its own.
Evidence label. Evidence is indirect
Applicability. Evidence is indirect — A clinical committee’s synthesis informs this caution; it does not validate self-diagnosis from a diary or single blood test.
Why no grade. A direct confidence grade is withheld because the available evidence is indirect for this reader-facing question.
Rationale. The 2026 ASRM committee opinion describes variation in definitions, short phases in fertile women and a lack of a reliable clinical test that distinguishes fertile from infertile women.
Limitations. This assessment uses the committee’s synthesis; its underlying studies were not individually reappraised here. It does not dismiss symptoms or known endocrine conditions and cannot diagnose an individual.
Safety context. Discuss persistent or disabling symptoms with a qualified clinician. These findings do not replace assessment or establish a personal diagnosis.
Method. Elara Evidence method, version 0.1.
Independent review pending
Search. Targeted verification of the supplied article citations and relevant clinical guidance on October 27, 2026. This was not a systematic literature search or a formal GRADE review. Access limits and correction notices are recorded for each source; absence of a notice is not a guarantee. Searched through .
This is a secondary assessment through the committee opinion, not a new appraisal of the app study. An LH surge is also not a guarantee of egg release. Contraceptive fertility-awareness methods require specific instruction and multiple signs. [10] Section cited: FERTILITY-AWARENESS METHODS
Question. Calendar app predictions and ovulation tracking and Identifying an exact ovulation day in People using cycle tracking to estimate ovulation.
Finding. Calendar predictions are estimates. They cannot confirm the exact day of ovulation or establish that unprotected sex is safe.
Evidence label. Evidence is indirect
Applicability. Evidence is indirect — The committee’s review concerns fertility tracking; it is not validation of a particular current app or a stand-alone contraceptive method.
Why no grade. A direct confidence grade is withheld because the available evidence is indirect for this reader-facing question.
Rationale. ASRM describes a study of 949 volunteers in which calendar apps had at most 21% accuracy for the ovulation day against urinary LH testing. It distinguishes calendar estimates, LH surges and temperature tracking.
Limitations. This is a secondary assessment through the committee opinion, not a new appraisal of the app study. An LH surge is also not a guarantee of egg release. Contraceptive fertility-awareness methods require specific instruction and multiple signs.
Safety context. Discuss persistent or disabling symptoms with a qualified clinician. These findings do not replace assessment or establish a personal diagnosis.
Method. Elara Evidence method, version 0.1.
Independent review pending
Search. Targeted verification of the supplied article citations and relevant clinical guidance on October 27, 2026. This was not a systematic literature search or a formal GRADE review. Access limits and correction notices are recorded for each source; absence of a notice is not a guarantee. Searched through .
Uncertain findings do not prove identical performance for every person. Pain, sleep and individual symptoms still matter. This evidence does not establish a universal phase-based training schedule. [18] Section cited: Methods; Discussion; Conclusions
Question. Menstrual-cycle phase and Acute strength and adaptations to resistance training in Young, healthy, naturally menstruating women represented in five reviews.
Finding. The reviewed evidence does not justify assuming that everyone is weaker in the luteal phase.
Evidence label. Limited confidence
Applicability. Directly applicable
Rationale. The 2023 umbrella review found inconsistent results across five reviews and substantial weaknesses in cycle verification and study methods.
Limitations. Uncertain findings do not prove identical performance for every person. Pain, sleep and individual symptoms still matter. This evidence does not establish a universal phase-based training schedule.
Safety context. Discuss persistent or disabling symptoms with a qualified clinician. These findings do not replace assessment or establish a personal diagnosis.
Method. Elara Evidence method, version 0.1.
Independent review pending
Search. Targeted verification of the supplied article citations and relevant clinical guidance on October 27, 2026. This was not a systematic literature search or a formal GRADE review. Access limits and correction notices are recorded for each source; absence of a notice is not a guarantee. Searched through .
Confidence describes how certain we are about a research finding. It does not measure how healthy a food is, or promise that it will work for you.
Stacie Brett writes and edits content for women’s health brands. She helps make articles and web pages easier to find and understand, focusing on the questions women want answered.
Full profile and articles ↗

