
ABOUT THE AUTHOR
Stacie Brett
Stacie Brett writes and edits content for women’s health brands. She helps make articles and web pages easier to find and understand, focusing on the questions women want answered.
Full profile and articles ↗Expert reviewed by Jasveer Matharu · 27 October 2026
Added evidence summaries for 7 recommendations.
Updated the fatigue guide, practical advice, cycle diagram and sources; credited Stacie Brett as writer and editor.
First published

If you notice yourself feeling tired after ovulation or running out of energy the week before your period, it can be frustrating, especially when your usual routine hasn’t changed. This is often described as luteal phase fatigue.
This guide explains what may be happening, what you can try and when it’s worth getting extra support.
Luteal phase fatigue is the tiredness and low energy that shows up in the second half of your menstrual cycle, between ovulation and your period.
You might notice tiredness at a different point in your cycle from someone else, or find that it changes from month to month. Tiredness is listed by the NHS as one of the common symptoms of PMS (opens in a new tab), alongside mood changes, bloating, breast tenderness and cravings.
The luteal phase starts when you ovulate and ends when your period begins. Its timing varies between people and cycles (opens in a new tab). Once the egg is released, the follicle (the small sac it grew in) turns into a temporary gland called the corpus luteum. This makes progesterone.
This hormone pattern describes cycles in which ovulation happens. The combined contraceptive pill usually stops ovulation (opens in a new tab), so the same phase-by-phase explanation doesn’t apply while you’re taking it. You can still use the practical suggestions below.
You may notice changes in energy across your cycle, but your experience can differ from someone else’s and from month to month. Tracking your own symptoms is a more useful starting point.
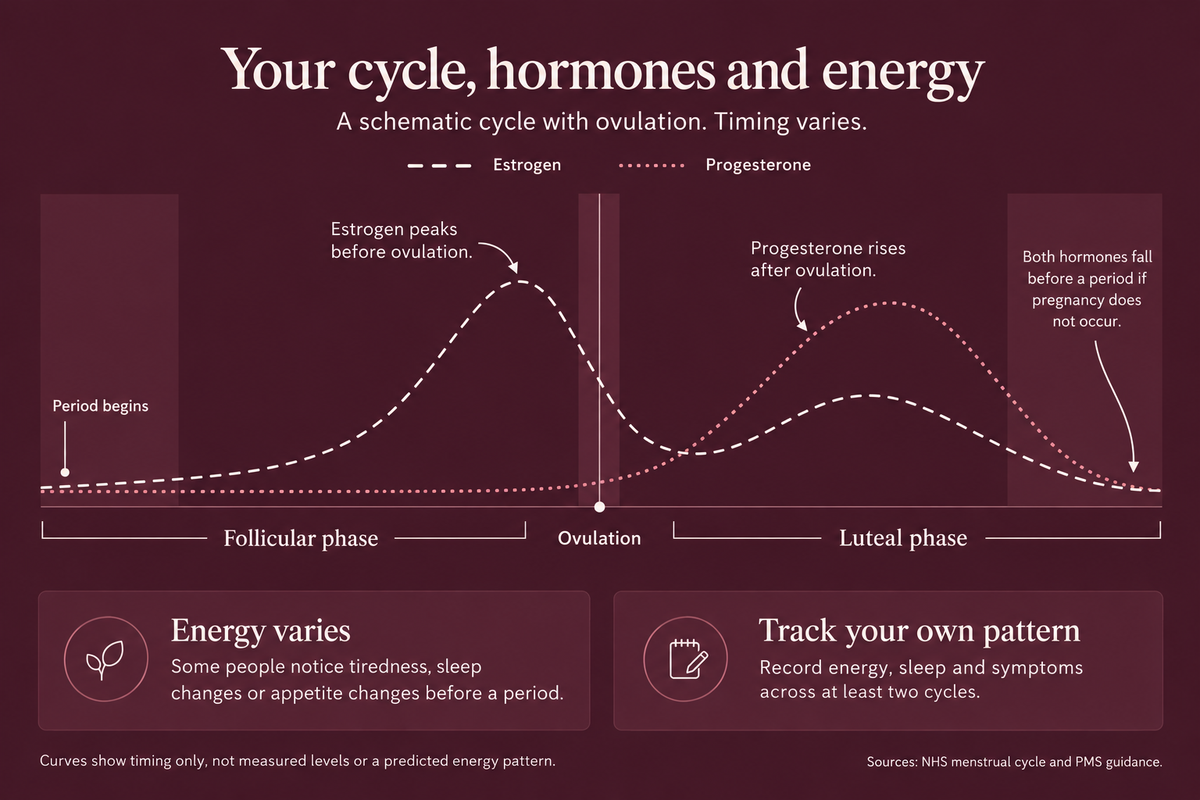
View full-size diagram (opens in a new tab)
Diagram references: NHS menstrual-cycle guidance (opens in a new tab) and NHS PMS guidance (opens in a new tab).
For more on the phases and the hormones behind them, see our guide to the menstrual cycle.
To help manage tiredness during the luteal phase, try eating regularly, protecting your sleep and adjusting activity to how you feel. If you notice a recurring pattern, planning around your own symptoms may also help.
| Phase | What’s happening | Options to try |
|---|---|---|
| Earlier luteal phase: after ovulation | Progesterone rises after ovulation and body temperature is slightly higher. Some people notice changes in appetite or sleep, but experiences vary. | Eat regularly and aim for a balanced diet across the day or week. Adjust workouts to your symptoms rather than automatically reducing intensity. Avoid caffeine close to bedtime. Schedule demanding tasks around your own energy pattern where possible. |
| Late luteal phase: the days before your period | Estrogen and progesterone fall before menstruation. PMS symptoms can occur before your period, but their timing and severity vary. | Keep meals varied and let your appetite guide you; you don’t need a special menu for these days. Adjust workouts to how you feel, just as you would earlier in the phase; rest when you need to. Protect bedtime. If you notice recurring symptoms, allow flexibility in your plans. Tracking may help you spot patterns. |
Use this table as a guide, rather than a timetable for how you should feel. If tiredness is severe, lasts all month, or comes with heavy periods, low mood or weight change, see a doctor.
You may notice you feel hungrier during the luteal phase. Research suggests that resting metabolism (the energy your body uses for functions such as breathing and circulation) may rise slightly after ovulation (opens in a new tab), although findings vary. If your usual meals aren’t leaving you satisfied, try a more substantial meal or a snack, such as yogurt with fruit or toast with peanut butter.
If you want the full breakdown of what to eat in each half of the luteal phase, including recipes, our nutrition guide has it.
When you’re tired and hungrier than usual, it’s understandable to reach for whatever is quick and easy. Some days, even deciding what to cook can feel like one task too many!
Keep meals simple: start with a carbohydrate such as bread, rice, pasta or potatoes for energy, then add a protein source, some fruit or vegetables and a little fat. That could be eggs on toast with tomatoes, or microwave rice with chickpeas, frozen vegetables and olive oil.
There’s room for a sugary snack too. You don’t need a special luteal-phase menu or a perfectly balanced plate at every meal. Instead, aim for variety and balance across the day or week (opens in a new tab). Shortcuts like frozen or canned fruit and vegetables can make that feel much more manageable.
Iron is also worth considering if you have heavy periods and feel tired beyond the premenstrual week. Iron deficiency anemia can cause tiredness (opens in a new tab). Your GP (a primary care doctor) can talk through your symptoms and arrange blood tests if needed.
Regular exercise may help with PMS symptoms, although the evidence is uncertain (opens in a new tab).
Adjust the intensity to how you feel; gentler activity can be an option on days when symptoms make your usual workout uncomfortable.
So what does that mean for your workout? If you feel up to your usual session, you don’t need to change it just because of where you are in your cycle. Check in with how you feel as you go, and adjust if you need to.
On days when your usual workout feels uncomfortable, a walk, yoga or a lighter strength session may feel more manageable. It’s also okay to rest when you need to.
You may feel tired but still struggle to get a good night’s sleep before your period. After ovulation, progesterone raises your body temperature slightly, and the usual overnight drop in temperature becomes less pronounced (opens in a new tab). This may contribute to changes in sleep. As your period approaches, symptoms such as anxiety, bloating or breast tenderness (opens in a new tab) can also make it harder to feel settled and comfortable.
Not everyone notices a change, but if your sleep suffers at this point in your cycle, give yourself a little extra support: keep your bedroom comfortably cool, make time to wind down and aim for consistent sleeping and waking times (opens in a new tab). Make room for the sleep you need; there isn’t a set number of extra hours everyone needs at this point in their cycle.
If you feel stressed as well as tired, try making room for a short break or a relaxing activity. The NHS suggests yoga or meditation as ways to reduce stress when managing PMS (opens in a new tab). Choose something that suits you, and consider postponing non-essential commitments when you need more breathing room. You could try:
Start with what you notice about your own energy. PMS symptoms can vary from person to person and from month to month (opens in a new tab), so use your own experience as a guide.
If you notice that some days tend to be harder, look for small ways to give yourself more breathing room. You could prepare a few meals in advance, leave gaps between commitments or move a demanding task to a day when you usually feel better, where that is possible.
Keep your plans flexible and check in with how you feel on the day. You don’t need to organize your whole month around your cycle, and it’s fine if your diary doesn’t reveal a consistent pattern.
The NHS recommends keeping a symptom diary for at least two menstrual cycles (opens in a new tab). You could record your energy out of ten, how you slept, other symptoms and when your period starts.
A diary may help you spot recurring patterns and discuss symptoms with your GP, although your experience can vary from month to month. And if tiredness is making everyday life difficult, speak to your GP, you don’t have to finish tracking first.
How do you feel during the luteal phase? Does your energy dip? Tell us in the poll below, or share what works for you in the comments.
There may be a few things going on at once. Hormonal changes, trouble sleeping and other premenstrual symptoms could all play a part in how you feel. There isn’t one explanation that fits everyone.
Progesterone given as a medicine can have a mild sedating effect (opens in a new tab), making people feel more tired. That doesn’t show how much natural hormone changes explain tiredness during your cycle.
After ovulation, body temperature rises slightly, and studies have also found a small increase in heart rate during sleep.
Core body temperature, the temperature deeper inside your body, is generally about 0.3 to 0.7°C higher after ovulation than before it (opens in a new tab). Progesterone contributes to this rise. A wrist-sensor study analyzed 708 cycles from 193 women. Average nighttime heart rate was approximately 3 to 4 beats per minute higher in the luteal phase than in the follicular phase (opens in a new tab), and wrist skin temperature was highest in the late luteal phase. Wrist temperature isn’t the same as core temperature, and these averages aren’t targets for your own readings.
These are small changes in how your body works. The wrist-sensor study measured cycle-related patterns, but did not establish that the increases in temperature or heart rate caused tiredness.
Some people report poorer sleep before their period (opens in a new tab), particularly if they also have premenstrual symptoms or painful cramps. However, studies do not consistently find more waking or fragmented sleep across the luteal phase. One study found only a small premenstrual difference in reported sleep quality (opens in a new tab), which was no longer statistically significant after accounting for stress and social support.
Sleep changes won’t feel the same for everyone. If yours suffers before your period, start with the practical ideas in “Protect your sleep” above. You don’t need to work out the exact hormonal cause before asking for help.
Your body may use slightly more energy at rest after ovulation, but findings vary (opens in a new tab). That doesn’t translate into a fixed amount of extra food everyone needs. If your usual meals aren’t leaving you satisfied, try a more substantial meal or add a snack.
Some people experience tiredness, low mood or irritability in the days before their period, but the timing and severity vary.
If there’s no pregnancy, the corpus luteum breaks down and progesterone and estrogen fall before menstruation. PMS can include tiredness, trouble sleeping, mood changes and cravings (opens in a new tab). That doesn’t mean your energy will rise and fall in step with progesterone. How you feel can be more complicated than that.
Some people feel more tired before their period. The NHS lists tiredness and trouble sleeping among the most common PMS symptoms (opens in a new tab), but these are not an inevitable part of every cycle.
What varies is how much it affects you. You might feel ready for bed a little earlier, or find that everyday tasks take more effort. But exhaustion that disrupts work, relationships or daily life shouldn’t be dismissed as something you simply have to put up with.
If that sounds familiar, speak to your GP, especially if you also experience intense low mood, anxiety or irritability before your period. These symptoms can occur with PMDD (opens in a new tab), but fatigue alone doesn’t mean you have it. Your GP can help you understand what’s happening and discuss support.
Hormone levels change throughout the luteal phase, but those changes do not give everyone the same timetable for tiredness.
Your own notes can help you work out whether there’s a pattern. You don’t need to fit your experience to particular days on a cycle chart.
If you’re feeling persistently drained, it’s worth discussing whether a nutrient deficiency could be contributing. That doesn’t mean you’ve been eating badly, and tiredness alone can’t tell you which nutrient, if any, is low.
A varied diet can help you get the nutrients you need. If you’re worried you might be low in something, your GP can help you work it out. They’ll consider how you’re feeling, what you eat and your medical history before deciding whether tests or treatment would help.
Speak to your GP if tiredness is persistent, unexplained or affecting daily life, whether or not it seems linked to your cycle. In particular, get it checked if:
If symptoms keep disrupting your life, a clinician can discuss treatments for PMS or PMDD as well as lifestyle changes (opens in a new tab). You don’t have to manage this on your own.
If you’re having a mental health crisis or feel unable to keep yourself safe, seek urgent help now. The NHS PMDD page includes guidance on getting urgent mental health support (opens in a new tab).
Hormonal changes, trouble sleeping and other premenstrual symptoms may all play a part. There isn’t one explanation that fits everyone, so it can help to note what else is happening when you feel tired.
Progesterone given as a medicine can make you feel tired. That doesn’t tell us how much the natural rise and fall of progesterone explains tiredness during your cycle.
Tiredness can occur as part of PMS, but not everyone experiences it. Exhaustion that stops you functioning, lasts all month, or comes with very low mood is worth getting checked out by a doctor.
It varies from person to person. Try noting when tiredness starts and when it eases, alongside your period dates. If it doesn’t let up or makes everyday life difficult, speak to your GP.
Your energy may pick up before your period, but a change in how you feel doesn’t tell you what caused it. Try noting when it happens rather than assuming it’s a direct response to falling progesterone.
You don’t need to push through exhaustion. Try gentler movement or rest, depending on how you feel. If exhaustion keeps happening or makes everyday life difficult, speak to your GP.
There isn’t a set amount of extra sleep everyone needs. If your sleep suffers before your period, give yourself time to wind down and try to keep regular sleeping and waking times.
Supplements may help if you have a deficiency that needs treatment, such as iron deficiency anemia. Evidence for magnesium and B6 supplements for PMS is limited (opens in a new tab). Check with your GP or pharmacist before starting supplements, particularly if you take medicines. High doses of vitamin B6 can damage nerves (opens in a new tab), so ask them to check the total amount across any supplements you take.
Explore the findings and sources for each recommendation.
We checked selected research claims about metabolism, exercise, progesterone, body temperature, heart rate and sleep.
Each explanation separates the finding from what it cannot tell us.
This draft contains 6 research assessments. Clinical self-care and safety advice is linked to guidance and checked separately in the review notes. It is not a systematic review or medical approval of the article.
Confidence describes how certain we are about a research finding. It does not measure how healthy a food is, or promise that it will work for you.
Search check: Targeted verification of the supplied article citations and relevant clinical guidance on October 27, 2026. This was not a systematic literature search or a formal GRADE review. Access limits and correction notices are recorded for each source; absence of a notice is not a guarantee. Searched through .
What the confidence labels meanSmall samples, differences in ovulation confirmation and measurement error limit precision. Resting metabolism is not total daily food need, and this research did not test whether extra food treats fatigue. [4] Section cited: Results; Discussion [20] Section cited: Abstract
Question. Follicular versus luteal menstrual phase and Resting energy expenditure, rather than a prescribed food allowance in Healthy, naturally menstruating adults.
Finding. Resting energy use may rise slightly after ovulation. The research does not establish a fixed extra calorie allowance.
Evidence label. Limited confidence
Applicability. Directly applicable
Rationale. The 2026 review included seven recent studies; four found significant increases. An older meta-analysis also found a small average rise, but its newer-study subgroup was not statistically significant.
Limitations. Small samples, differences in ovulation confirmation and measurement error limit precision. Resting metabolism is not total daily food need, and this research did not test whether extra food treats fatigue.
Safety context. Discuss persistent or disabling symptoms with a qualified clinician. These findings do not replace assessment or establish a personal diagnosis.
Method. Elara Evidence method, version 0.1.
Independent review pending
Search. Targeted verification of the supplied article citations and relevant clinical guidance on October 27, 2026. This was not a systematic literature search or a formal GRADE review. Access limits and correction notices are recorded for each source; absence of a notice is not a guarantee. Searched through .
Most trials had high risk of bias, results varied substantially, and programs lasted 8–12 weeks. None restricted exercise to the luteal phase. These results do not establish a best workout or a need to push through exhaustion. [9] Section cited: Primary outcome; Strengths and limitations; Intervention characteristics
Question. Regular exercise compared with non-exercise control and Overall premenstrual symptoms in Women with PMS in the included trials.
Finding. Regular exercise may reduce PMS symptoms. It is not established as an immediate treatment for luteal-phase exhaustion.
Evidence label. Limited confidence
Applicability. Directly applicable
Rationale. The review included 15 trials with 717 participants. Seven trials, with 265 participants, contributed to the pooled overall symptom result.
Limitations. Most trials had high risk of bias, results varied substantially, and programs lasted 8–12 weeks. None restricted exercise to the luteal phase. These results do not establish a best workout or a need to push through exhaustion.
Safety context. Discuss persistent or disabling symptoms with a qualified clinician. These findings do not replace assessment or establish a personal diagnosis.
Method. Elara Evidence method, version 0.1.
Independent review pending
Search. Targeted verification of the supplied article citations and relevant clinical guidance on October 27, 2026. This was not a systematic literature search or a formal GRADE review. Access limits and correction notices are recorded for each source; absence of a notice is not a guarantee. Searched through .
Question. Natural luteal progesterone changes, informed by a medication experiment and Feelings of fatigue in People with naturally occurring luteal-phase tiredness.
Finding. Progesterone medication can have modest sedating effects. Its role in everyday cycle-related tiredness remains uncertain.
Evidence label. Evidence is indirect
Applicability. Evidence is indirect — An injected dose in men and early-follicular women cannot quantify the effect of naturally changing progesterone in the luteal phase.
Why no grade. A direct confidence grade is withheld because the available evidence is indirect for this reader-facing question.
Rationale. Seven women in the early follicular phase and ten men received a 200 mg progesterone injection or placebo. The abstract reports small increases in fatigue and some impairment of eye pursuit.
Limitations. This was an acute medication experiment, not a study of natural luteal-phase fatigue. Only the abstract was assessed.
Safety context. Discuss persistent or disabling symptoms with a qualified clinician. These findings do not replace assessment or establish a personal diagnosis.
Method. Elara Evidence method, version 0.1.
Independent review pending
Search. Targeted verification of the supplied article citations and relevant clinical guidance on October 27, 2026. This was not a systematic literature search or a formal GRADE review. Access limits and correction notices are recorded for each source; absence of a notice is not a guarantee. Searched through .
Measurement site, illness, sleep and environment affect readings. Wrist skin temperature is not core temperature. This does not predict an exact ovulation date, establish safe contraceptive days or prove a cause of fatigue. [13] Section cited: Effect of the menstrual cycle on core body temperature; Determining menstrual cycle phase
Question. Hormone changes in ovulatory cycles and Core temperature after ovulation and retrospective cycle clues in Naturally menstruating women in physiology studies.
Finding. Core temperature is commonly higher after ovulation. A sustained rise can provide a retrospective clue that ovulation occurred.
Evidence label. Moderate confidence
Applicability. Directly applicable
Rationale. The review describes an increase of about 0.3–0.7°C compared with the follicular phase, particularly evident during sleep or on waking.
Limitations. Measurement site, illness, sleep and environment affect readings. Wrist skin temperature is not core temperature. This does not predict an exact ovulation date, establish safe contraceptive days or prove a cause of fatigue.
Safety context. Discuss persistent or disabling symptoms with a qualified clinician. These findings do not replace assessment or establish a personal diagnosis.
Method. Elara Evidence method, version 0.1.
Independent review pending
Search. Targeted verification of the supplied article citations and relevant clinical guidance on October 27, 2026. This was not a systematic literature search or a formal GRADE review. Access limits and correction notices are recorded for each source; absence of a notice is not a guarantee. Searched through .
The selected observational sample and commercial-device study do not establish a cause of tiredness or a target for personal readings. Several authors worked for the device manufacturer. Wrist and core temperature are different measures. [14] Section cited: Population Characteristics; Heart Rate
Question. Menstrual-cycle phase and Nighttime heart rate measured by a wrist device in 193 participants contributing 708 eligible cycles, generally trying to conceive.
Finding. Average nighttime heart rate was higher in the luteal phase in this wearable study.
Evidence label. Limited confidence
Applicability. Directly applicable
Rationale. Mean heart rate was about 56.6 beats per minute in the follicular phase and 60.0–60.5 in the luteal phase: roughly 3–4 beats higher.
Limitations. The selected observational sample and commercial-device study do not establish a cause of tiredness or a target for personal readings. Several authors worked for the device manufacturer. Wrist and core temperature are different measures.
Safety context. Discuss persistent or disabling symptoms with a qualified clinician. These findings do not replace assessment or establish a personal diagnosis.
Method. Elara Evidence method, version 0.1.
Independent review pending
Search. Targeted verification of the supplied article citations and relevant clinical guidance on October 27, 2026. This was not a systematic literature search or a formal GRADE review. Access limits and correction notices are recorded for each source; absence of a notice is not a guarantee. Searched through .
Both papers were assessed through their abstracts. Self-rated sleep and laboratory measurements answer different questions. The evidence does not define extra hours of sleep everyone needs or a single hormonal cause. [10] Section cited: Abstract [15] Section cited: Abstract
Question. Menstrual-cycle phase and Subjective sleep quality and objective sleep changes in Women in sleep studies; symptoms and populations varied.
Finding. Some women report poorer sleep before a period. Objective sleep findings and individual experiences vary.
Evidence label. Limited confidence
Applicability. Directly applicable
Rationale. The 2018 review describes subjective and objective changes. In a 76-woman cohort covering 395 cycles, the small premenstrual difference in self-rated sleep was no longer significant after stress and social support were included.
Limitations. Both papers were assessed through their abstracts. Self-rated sleep and laboratory measurements answer different questions. The evidence does not define extra hours of sleep everyone needs or a single hormonal cause.
Safety context. Discuss persistent or disabling symptoms with a qualified clinician. These findings do not replace assessment or establish a personal diagnosis.
Method. Elara Evidence method, version 0.1.
Independent review pending
Search. Targeted verification of the supplied article citations and relevant clinical guidance on October 27, 2026. This was not a systematic literature search or a formal GRADE review. Access limits and correction notices are recorded for each source; absence of a notice is not a guarantee. Searched through .
Confidence describes how certain we are about a research finding. It does not measure how healthy a food is, or promise that it will work for you.
Stacie Brett writes and edits content for women’s health brands. She helps make articles and web pages easier to find and understand, focusing on the questions women want answered.
Full profile and articles ↗

